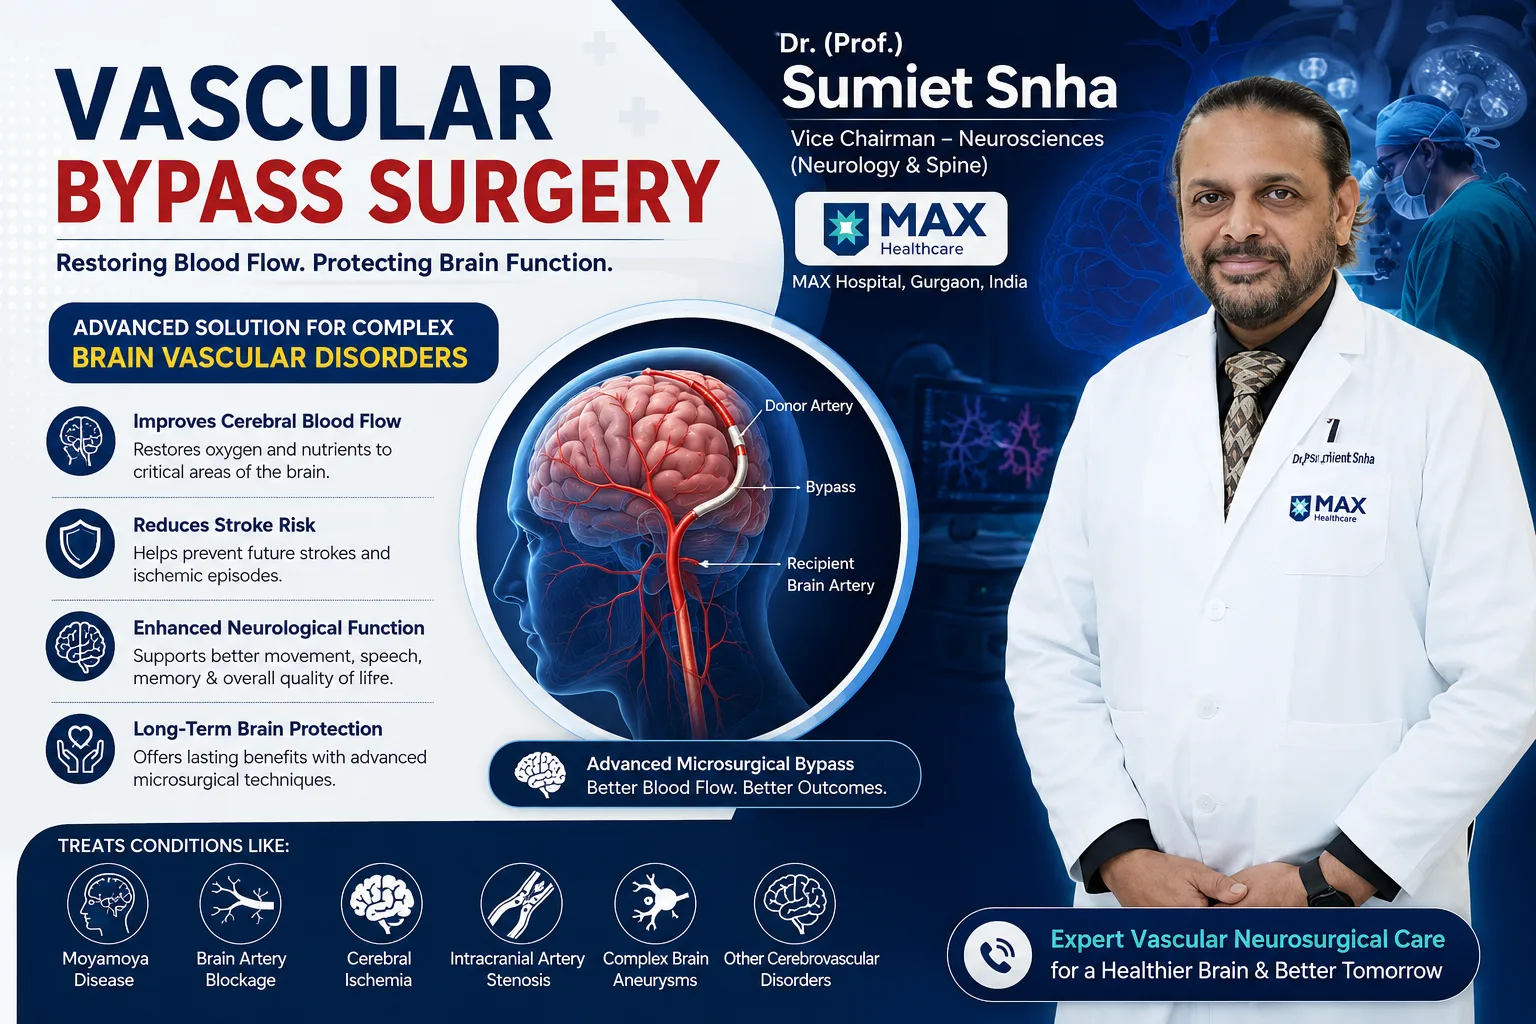
The brain cannot store oxygen or glucose. It depends every second on a steady flow of blood through its arteries. When a major brain artery becomes progressively narrowed or blocked - or when an artery must be sacrificed to treat a complex aneurysm or tumor - parts of the brain may be at risk of stroke. Cerebral bypass surgery, also called brain revascularization, creates a new pathway for blood to reach the brain, much like a heart bypass restores blood flow to the heart muscle. It is one of the most delicate operations in neurosurgery, requiring microsurgical skill to join blood vessels only one or two millimetres in diameter.
Dr. (Prof.) Sumiet Snha, former Professor of Neurosurgery at AIIMS, New Delhi, and Principal Director - Neurosurgery & Spine Surgery at Max Hospital, Dwarka, performs vascular bypass surgery as part of his cerebrovascular practice. His training includes work with Prof. Hiroshi Sano in Japan - a country with extensive experience in moyamoya disease and bypass techniques - and he received the Young Neurosurgeon Award to attend the International Conference on Cerebrovascular Surgery in Nagoya. This page explains when bypass surgery is needed, how it is performed and what recovery involves.

What Is Cerebral Bypass Surgery?
In a cerebral bypass, the surgeon connects a blood vessel from outside the brain (or another brain artery) to an artery on the brain's surface beyond the narrowed or blocked segment. Blood can then flow through this new connection to supply the brain tissue that was at risk. Bypasses are classified by the source of blood flow and the amount of flow they provide:
Low-flow bypass (STA-MCA)
The superficial temporal artery (STA) - the pulsing artery in front of the ear - is connected to a branch of the middle cerebral artery (MCA) on the brain surface. Commonly used in moyamoya disease and selected cases of carotid occlusion.
High-flow bypass
A graft (usually a segment of the radial artery from the forearm or a vein from the leg) carries blood from the external carotid artery in the neck to a larger brain artery. Used when an entire major artery must be replaced, as in some giant aneurysms.
Intracranial-intracranial (IC-IC) bypass
Two brain arteries are joined together directly within the skull, used in selected complex aneurysm reconstructions.
Indirect revascularization
Tissue rich in blood vessels - such as scalp artery, muscle or dura - is laid on the brain surface to encourage new vessel growth over time. Common in children with moyamoya.
Direct and indirect techniques are often combined, especially in moyamoya disease, to provide both immediate and long-term improvement in blood supply.
Conditions That May Need Bypass Surgery
Moyamoya disease and moyamoya syndrome
Moyamoya is a progressive condition in which the internal carotid arteries and their main branches at the base of the brain gradually narrow and close. In response, the brain develops a network of tiny, fragile collateral vessels that look like a "puff of smoke" on angiography - "moyamoya" in Japanese. It affects both children and adults. Children commonly present with transient ischaemic attacks (TIAs) or strokes, often triggered by crying, blowing (for example, into a whistle or hot food) or hyperventilation. Adults may present with strokes or with bleeding from the fragile collateral vessels. When the condition is associated with other diseases, such as Down syndrome, sickle cell disease or neurofibromatosis, it is called moyamoya syndrome.
Complex and giant aneurysms
Some aneurysms are too large, too wide or too complex to be clipped or coiled while preserving the parent artery. In such cases, the aneurysm may be treated by closing off the parent artery (trapping) - but first, a bypass is created to maintain blood flow to the brain territory beyond it. Bypass allows these challenging aneurysms to be treated definitively.
Skull base tumors involving arteries
Occasionally, tumors encase a major artery so that complete removal would require sacrificing it. A bypass can protect the brain's blood supply in these rare situations.
Symptomatic carotid or middle cerebral artery occlusion
Most people with a blocked carotid artery are best treated with medicines. However, a small group of carefully selected patients who continue to have symptoms due to insufficient blood flow ("haemodynamic insufficiency") despite optimal medical therapy may be considered for bypass, based on specialised perfusion studies.
Symptoms That Suggest Reduced Blood Flow to the Brain
- Transient ischaemic attacks - brief episodes of weakness, numbness, speech difficulty or visual loss that resolve within minutes to hours.
- Stroke - persistent weakness, facial droop, speech or vision problems.
- Recurrent headaches, particularly in moyamoya disease.
- Seizures.
- Involuntary movements (in some children with moyamoya).
- Cognitive decline, poor school performance or developmental delay in children.
- Symptoms triggered by dehydration, exertion, low blood pressure or hyperventilation.
Transient symptoms are a warning
A TIA may last only a few minutes, but it is a warning that a stroke may follow. Anyone with sudden weakness, numbness, speech or vision problems - even if they resolve - should seek urgent medical evaluation.
How the Need for Bypass Is Evaluated
Deciding whether a patient will benefit from bypass surgery requires detailed information about the blood vessels and, critically, about how well the brain is being supplied with blood.
- MRI brain with diffusion and perfusion sequences - identifies old and new strokes and areas of reduced blood flow.
- CT or MR angiography - shows narrowed or blocked arteries.
- Digital subtraction angiography (DSA) - the gold standard, showing the detailed anatomy of arteries, collaterals and potential donor vessels such as the superficial temporal artery.
- Perfusion studies with vasodilatory challenge - techniques such as CT/MR perfusion with acetazolamide or SPECT assess "cerebrovascular reserve" - the brain's ability to increase blood flow when needed. Poor reserve indicates a higher stroke risk and a greater likelihood of benefit from bypass.
- Neurological and cognitive assessment - establishes baseline function.
- Evaluation of associated conditions - blood tests, cardiac assessment and, in moyamoya syndrome, evaluation of related diseases.
Medical Management
Not every patient needs surgery. Medical treatment aims to reduce the risk of stroke and includes:
- Antiplatelet medicines such as aspirin (in selected patients, particularly with ischaemic presentations).
- Careful blood pressure management - avoiding both high pressure and sudden drops.
- Maintaining good hydration, especially in children with moyamoya.
- Control of cholesterol, diabetes and other vascular risk factors in adults.
- Stopping smoking.
- Avoiding triggers such as hyperventilation in moyamoya.
In moyamoya disease, however, medicines do not stop the progressive narrowing, and for patients with symptoms and reduced blood flow, surgical revascularization is generally recommended to reduce the risk of future strokes.
The Bypass Operation - Step by Step (STA-MCA Bypass)
- Preparation: the course of the superficial temporal artery is mapped on the scalp using Doppler ultrasound. Antiplatelet medicine is often continued.
- Anaesthesia: general anaesthesia with close control of blood pressure and carbon dioxide levels to protect the brain's blood flow.
- Harvesting the donor artery: the STA is carefully dissected from the scalp under the microscope, preserving its blood flow.
- Craniotomy: a small window of bone is removed, and the dura is opened to expose a suitable branch of the middle cerebral artery on the brain surface.
- Microvascular anastomosis: the recipient artery is temporarily clamped for a few minutes, a tiny opening is made, and the end of the STA is sewn to it using sutures finer than a human hair under high magnification.
- Checking the bypass: fluorescence angiography (ICG) and micro-Doppler confirm that blood is flowing through the new connection.
- Indirect augmentation (if planned): dura, muscle or other tissue is placed on the brain surface to encourage additional new vessel growth.
- Closure: the bone flap is replaced with an opening that avoids compressing the bypass vessel.
High-flow bypasses follow similar principles but involve harvesting a graft from the forearm or leg and connecting it between the neck and the brain arteries.
Indirect Revascularization in Children
In young children, the brain arteries may be too small for direct bypass. Indirect techniques are therefore widely used. In encephalo-duro-arterio-synangiosis (EDAS), the scalp artery with a cuff of tissue is laid directly on the brain surface; in encephalo-myo-synangiosis (EMS), a flap of temporalis muscle is placed on the brain; and in techniques involving multiple burr holes or the dura, the brain is exposed to vascular tissue at several points. Over the following months, new blood vessels grow from these tissues into the brain, improving blood supply. Children often respond very well to indirect revascularization, with a significant reduction in TIAs and strokes.
Benefits of Bypass Surgery
- Stroke prevention - in symptomatic moyamoya disease, revascularization significantly reduces the risk of future ischaemic strokes.
- Reduced bleeding risk - in adults with haemorrhagic moyamoya, direct bypass has been shown to reduce the risk of re-bleeding by relieving stress on fragile collateral vessels.
- Improved blood flow and symptoms - fewer TIAs, headaches and, in children, better developmental and school outcomes.
- Safe treatment of complex aneurysms that could not otherwise be treated without risking a stroke.
- Durability - successful bypasses often remain open and functional for many years.
Risks of Bypass Surgery
Bypass surgery is complex and carries risks that are discussed carefully with each patient:
- Stroke around the time of surgery - the brain in these patients is vulnerable to changes in blood pressure and carbon dioxide levels.
- Bleeding, including intracerebral haemorrhage.
- Hyperperfusion syndrome - a temporary state of excessive blood flow to a previously starved area, which may cause headache, seizures or temporary neurological symptoms; it is managed with careful blood pressure control.
- Bypass occlusion (the new connection closing).
- Wound healing problems on the scalp, particularly where the donor artery was harvested.
- Seizures and infection.
Meticulous anaesthesia, microsurgical technique and post-operative monitoring in a neuro-ICU minimise these risks.
Recovery After Bypass Surgery
What to expect
- ICU monitoring: typically for the first 24-48 hours, with close control of blood pressure and hydration.
- Hospital stay: usually around a week.
- Avoid pressure on the bypass: no tight headbands, spectacles pressing on the temple, or lying directly on the operated side of the head for a period, as advised.
- Medicines: antiplatelet therapy is usually continued; blood pressure targets are individualised.
- Imaging: follow-up angiography or CT angiography confirms that the bypass is working; perfusion studies may show improved blood flow over months.
- Return to activity: gradual return to school or work over 4-8 weeks.
Moyamoya Disease in India
Moyamoya disease was first described in Japan and is most frequently reported in East Asian populations, but it is increasingly recognised in India and other countries as awareness and imaging improve. Indian patients often present with ischaemic symptoms, and both children and adults are affected. Because the condition is uncommon, patients may see several doctors before the diagnosis is made. Any child with unexplained strokes or TIAs - particularly episodes triggered by crying or exertion - should be evaluated for moyamoya and other cerebral arteriopathies.
Living With Moyamoya After Surgery
After revascularization, most patients return to normal daily activities, school or work. Long-term care includes regular follow-up, maintaining hydration, avoiding dehydration during illness or hot weather, managing blood pressure, taking antiplatelet medicines as prescribed and informing any future anaesthetist about the condition, since anaesthesia for other procedures requires special precautions. Moyamoya is often bilateral, and the second side may need treatment if symptoms or reduced blood flow develop. With appropriate treatment and follow-up, many patients lead full, active lives.
Bypass for Complex Aneurysms - A Closer Look
Giant aneurysms, fusiform (spindle-shaped) aneurysms, blister aneurysms and some recurrent aneurysms cannot always be treated by clipping the neck or by endovascular methods. In these situations, a strategy of flow replacement and aneurysm exclusion may be the safest route: a bypass is created first to guarantee blood supply to the brain beyond the aneurysm, and the aneurysm and its parent artery are then closed off by clips or endovascular occlusion. Detailed planning includes test occlusion studies to assess how well the brain tolerates closure of the artery, which helps decide whether a low-flow or high-flow bypass is needed. Although these are among the most demanding procedures in neurosurgery, they offer a definitive solution for aneurysms that would otherwise carry a high risk of rupture or growth.
Why Choose Dr. (Prof.) Sumiet Snha for Bypass Surgery?
- AIIMS-trained neurosurgeon - MBBS, MS, DNB, MCh (AIIMS, New Delhi), FACS - with over 25 years of experience in brain and spine surgery.
- Training in cerebrovascular surgery with Prof. Hiroshi Sano, Japan, and Young Neurosurgeon Award for the 9th International Conference on Cerebrovascular Surgery, Nagoya.
- Former Professor of Neurosurgery, AIIMS, New Delhi, and founder faculty in-charge of its cadaver training facility, where microvascular skills are practised and taught.
- Integrated management of complex vascular lesions together with neuro-interventional and neuro-critical care teams.
- Advanced microsurgical infrastructure including ICG angiography and micro-Doppler at Max Super Speciality Hospital, Dwarka.
Factors Affecting the Cost of Cerebral Bypass Surgery
- Type of bypass - low-flow, high-flow, IC-IC or indirect.
- Whether one or both sides are treated.
- Pre-operative evaluation including angiography and perfusion studies.
- ICU and hospital stay.
- Associated procedures, such as aneurysm treatment.
- Insurance coverage.
Understanding Cerebrovascular Reserve
A central concept in deciding on bypass is cerebrovascular reserve - the brain's built-in ability to increase its blood flow when demand rises. In healthy people, small brain arteries dilate automatically to keep blood flow steady even if blood pressure falls. When a major artery is blocked, these small vessels may already be maximally dilated just to maintain normal flow at rest. The brain then has no reserve left: any further drop in blood pressure, dehydration or increased demand can tip it into ischaemia and stroke.
Perfusion imaging with a vasodilatory challenge measures this reserve. After a baseline scan, a medicine such as acetazolamide is given, which normally causes brain blood flow to increase. If flow in an area fails to rise - or even falls, a phenomenon known as "steal" - the reserve is exhausted, and that region is at high risk. Patients with exhausted reserve are the ones most likely to benefit from bypass, while those with preserved reserve are often best managed with medicines alone. This physiological approach helps avoid unnecessary surgery and targets treatment to patients who stand to gain the most.
Anaesthesia - A Crucial Part of Safe Bypass Surgery
Because the brain in moyamoya and occlusive disease is so dependent on stable blood flow, anaesthesia management is as important as the surgery itself. The anaesthesia team maintains blood pressure at or slightly above the patient's usual level, avoids low carbon dioxide levels (hyperventilation, which constricts brain vessels), keeps the patient well hydrated and warm, and ensures smooth waking without surges in blood pressure. In children, anxiety and crying before surgery are minimised, since crying causes hyperventilation that can trigger ischaemia. This careful teamwork significantly reduces the risk of stroke around the time of surgery.
Recognising Moyamoya in Children - Advice for Parents
Parents are often the first to notice that something is wrong. Warning signs include episodes of weakness in an arm or leg, facial drooping or slurred speech that come and go, particularly after crying, blowing into a balloon or whistle, blowing on hot food, or vigorous exercise. Some children have recurrent headaches, seizures, involuntary movements or a decline in school performance. Because these episodes may be brief and resolve completely, they are sometimes dismissed. Any such episode deserves prompt medical evaluation, including MRI and angiography where indicated. Early treatment, before permanent strokes occur, gives children the best chance of normal development.
Carotid Artery Disease - Where Bypass Fits In
Narrowing of the carotid arteries in the neck, usually due to atherosclerosis, is a common cause of stroke in adults. Most patients are treated with antiplatelet medicines, statins, blood pressure control and lifestyle changes. Those with significant narrowing that has caused symptoms may benefit from carotid endarterectomy (surgical removal of the plaque) or carotid stenting. When the carotid artery is completely blocked, these procedures are generally not possible, and treatment focuses on medicines. Large clinical trials have shown that bypass surgery is not beneficial for most patients with carotid occlusion. However, in a small subgroup who continue to have strokes or TIAs despite optimal medical therapy and who show severely impaired cerebrovascular reserve on perfusion testing, bypass may be considered in experienced centres after careful discussion. This individualised approach avoids overtreatment while offering an option to those who truly need it.
Life After Revascularization - Long-Term Follow-Up
After bypass surgery, follow-up is typically arranged at a few weeks, then at around three to six months with imaging to confirm the function of the bypass, and periodically thereafter. Perfusion studies may show progressive improvement in blood flow as indirect collaterals develop. Children continue developmental and school assessments. Patients should maintain good hydration, especially during fever, diarrhoea or hot weather, avoid smoking, keep blood pressure within the target range, and continue prescribed medicines. Any new neurological symptom should be reported promptly. With these measures, most patients enjoy long periods free of strokes and return to school, work and family life with confidence.
Key Terms
- STA-MCA bypass: connection of the superficial temporal artery to a middle cerebral artery branch.
- Anastomosis: the surgical joining of two blood vessels.
- EDAS / EMS: indirect revascularization techniques using scalp artery or muscle tissue.
- Hyperperfusion: a temporary excess of blood flow after revascularization.
- Cerebrovascular reserve: the brain's capacity to increase blood flow when needed.
Direct, Indirect and Combined Revascularization Compared
Families often ask why one patient receives a direct bypass while another, with the same diagnosis, is offered an indirect procedure. The answer lies in the size of the recipient arteries, the age of the patient, how urgently extra blood flow is needed and the overall pattern of disease on angiography. Each technique has its own strengths, and in many patients with moyamoya the two are combined in a single operation so that the brain receives immediate flow from the direct connection and additional, longer-term collateral growth from the indirect tissue. The table below summarises the key practical differences.
| Feature | Direct bypass (e.g. STA-MCA) | Indirect revascularization (e.g. EDAS, EMS) |
|---|---|---|
| When extra blood flow begins | Immediately after the connection is completed | Gradually, as new vessels grow over the following months |
| Recipient artery needed | Yes - usually at least about a millimetre in diameter | No - tissue is simply laid on the brain surface |
| Typical patients | Adults, older children, haemorrhagic moyamoya, aneurysm reconstruction | Young children, patients with very small or fragile arteries |
| Technical demand | High - requires microvascular suturing | Lower, though careful handling of the donor tissue is essential |
| Main early concern | Hyperperfusion or bypass occlusion | Stroke risk persists until collaterals mature |
No single technique is "best" for everyone. The plan is individualised after reviewing the angiogram, perfusion results and the patient's clinical picture, and the reasons for the recommended approach are explained in plain language before any decision is made.
Preparing for Your Bypass Operation
Good preparation reduces avoidable risks and helps the day of surgery run smoothly. In the days before admission, patients are usually asked to continue their antiplatelet medicine unless told otherwise, to drink fluids generously, and to avoid situations that could cause dehydration. Any fever, diarrhoea or new neurological symptom in the lead-up to surgery should be reported, as the operation may need to be rescheduled until the patient is well. Blood thinners other than those specifically advised, herbal supplements and some pain medicines may need to be stopped, so a complete list of current medicines should be shared with the team.
A simple checklist for patients and families
- Bring all previous scans, angiography films or discs and reports, including perfusion studies.
- Carry a list of medicines, allergies and any previous reactions to anaesthesia or contrast dye.
- Avoid hair dyes or scalp treatments in the week before surgery, as the scalp artery will be used.
- For children, bring a comforting toy and plan how a parent can stay close to reduce crying and anxiety.
- Arrange for a family member to stay during the hospital admission and the first weeks at home.
- Note down questions in advance so nothing important is forgotten during the pre-operative discussion.
Seeking an Opinion From Outside Delhi
Moyamoya disease and complex aneurysms needing bypass are uncommon, and many patients live in cities where cerebrovascular bypass is not routinely performed. A preliminary opinion does not always require travel. Patients and families can share MRI, angiography and perfusion reports by WhatsApp on +91-8448877746 or by email at sumitneuro@gmail.com, and a video consultation can then be arranged to discuss the findings and the likely options. This helps families understand whether further tests or an in-person visit are needed before making travel plans.
When a visit is required, Max Super Speciality Hospital in Dwarka is conveniently located close to IGI Airport, which makes it practical for patients flying in from other states or from abroad. The Dwarka Expressway provides a direct link from Gurugram, and the Blue Line of the Delhi Metro serves the area. The OPD runs from Monday to Saturday. To plan a visit, you can book an appointment or use the contact page. For related conditions, see our pages on vascular neurosurgery and paediatric neurosurgery.
Frequently Asked Questions
What is a brain bypass surgery?
It is an operation that creates a new pathway for blood to reach the brain, usually by connecting a scalp artery to a brain artery, to bypass a narrowed or blocked vessel.
Who needs cerebral bypass surgery?
Patients with symptomatic moyamoya disease, certain complex aneurysms that require parent artery sacrifice, and selected patients with reduced brain blood flow despite best medical treatment.
Is bypass surgery safe for children?
Yes. Children with moyamoya are commonly treated with indirect or combined revascularization, which significantly reduces the risk of future strokes.
How long does the bypass last?
Successful bypasses often remain open and functional for many years. Follow-up imaging checks the bypass and blood flow.
Will I need to take medicines after surgery?
Most patients continue antiplatelet medicines such as aspirin, along with blood pressure and risk-factor management as advised.
Can moyamoya disease be cured?
The underlying arterial narrowing cannot be reversed, but revascularization surgery restores blood supply and substantially lowers the risk of strokes.
Is this the same as a heart bypass?
The principle is similar - rerouting blood around a blocked artery - but brain bypass involves much smaller vessels and microsurgical techniques.
Protect Your Brain's Blood Supply
If you or your child has been diagnosed with moyamoya disease, a complex aneurysm or reduced blood flow to the brain, a specialist evaluation will clarify whether revascularization is appropriate. Book a consultation with Dr. (Prof.) Sumiet Snha at Max Hospital, Dwarka, New Delhi. Related reading: vascular neurosurgery, paediatric neurosurgery and epilepsy surgery.